
Nutritional Assessment for Cancer Patients: Body Measurements, Blood Markers, SGA and Practical Diet Care
- Malnutrition in cancer affects treatment tolerance, recovery and quality of life.
- Assessment combines weight history, body measurements, blood markers and tools such as SGA.
- Diet care should be tailored to symptoms, with supplements or tube feeding when eating is not enough.
Contents
- Why cancer patients become malnourished
- Step 1: weight history and BMI
- Step 2: body measurements
- Step 3: blood markers
- Step 4: Subjective Global Assessment
- Step 5: diet care by symptom
- Who does what in the team
- A worked case
- Refeeding syndrome: the risk when feeding restarts
- Nutrition across the treatment journey
- How much energy and protein?
- FAQ
Weight loss is one of the most common problems in cancer care, and malnutrition makes chemotherapy and surgery harder to tolerate. That is why nutritional assessment is a core topic in clinical nutrition, oncology nursing and dietetics modules. This guide follows the usual order of an assessment: history and measurements, blood tests, a structured tool, then a care plan built around the patient's symptoms.
Why cancer patients become malnourished
The tumour itself changes metabolism, releasing inflammatory signals that break down muscle and fat. Treatment adds nausea, mouth ulcers, taste changes, diarrhoea and fatigue, while anxiety and low mood blunt appetite further. Tumours of the head and neck, oesophagus, stomach and pancreas carry the highest risk because they interfere directly with eating or digestion.
Student money tip from CampusDown Repair UpHow to Plan a Home Repair Budget — A practical, step-by-step way to plan a home repair budget: define the scope, price it, add a contingency, rank repairs by urgency and…
Severe, ongoing loss is described as cancer cachexia. The international consensus published by Fearon and colleagues in 2011 defines it as weight loss of more than 5% over six months, or more than 2% in someone who already has a BMI under 20 or low muscle mass. Unlike simple starvation, cachexia cannot be fully reversed by feeding alone, which is why early detection matters.

Step 1: weight history and BMI
Start with what the patient weighed before they became unwell. Unintentional loss of 5% or more in one month, or 10% or more in six months, is a red flag. For example, someone who has gone from 70 kg to 63 kg has lost 7 kg, which is 10% of their usual weight.
Body mass index (weight in kg divided by height in metres squared) is quick but blunt. Under the WHO categories, below 18.5 is underweight and 30 or above is obese. A patient with a normal or high BMI can still be losing muscle rapidly, so BMI must always be read alongside the weight trend. The CampusDown BMI calculator is handy for checking practice cases.

Skimming the section headings first makes a long guide much easier to map out. Try writing down one question of your own as you read.
Step 2: body measurements
When a patient is bed-bound or has oedema that hides weight loss, arm measurements help. Mid-upper arm circumference (MAC) reflects both fat and muscle; triceps skinfold thickness (TSF), measured with calipers, estimates fat stores. Mid-arm muscle circumference is then calculated as MAMC = MAC − (3.14 × TSF), with both values in centimetres, giving an estimate of muscle mass. Repeating the same measurement over time is more informative than any single reading.
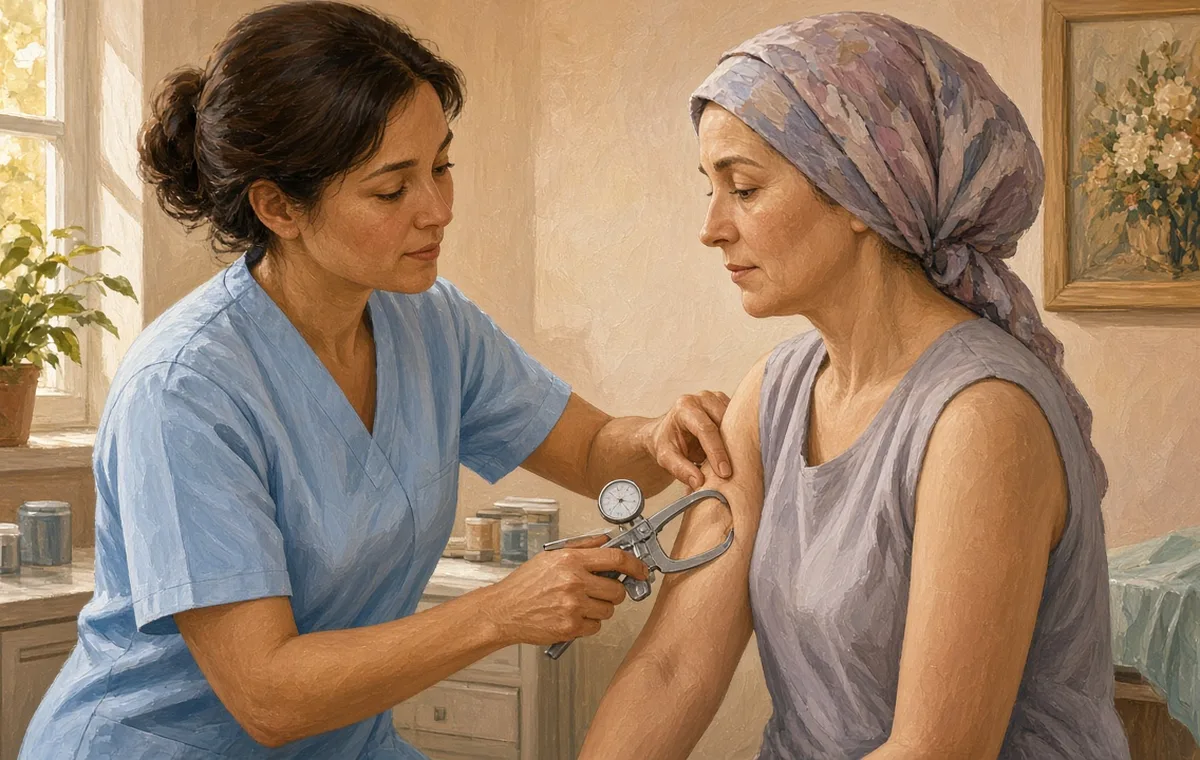
Step 3: blood markers
| Marker | Approximate half-life | What it tells you |
|---|---|---|
| Albumin | About 3 weeks | Long-term status and prognosis; slow to change |
| Transferrin | About 8 days | Medium-term change; affected by iron status |
| Prealbumin (transthyretin) | About 2 days | Short-term response to feeding |
All three fall during inflammation, regardless of what the patient eats, so always check C-reactive protein (CRP) at the same time. A low albumin with a very high CRP says more about inflammation than about diet.
Step 4: Subjective Global Assessment
SGA, described by Detsky and colleagues in 1987, combines history (weight change, intake, gastrointestinal symptoms, functional capacity) with a physical examination for loss of fat and muscle and for fluid retention. The clinician then grades the patient: A, well nourished; B, moderately malnourished or at risk; C, severely malnourished. A patient-generated version, PG-SGA, is widely used in oncology. In UK practice, screening is often done first with MUST from BAPEN, and those who score as high risk go on to a full dietetic assessment.
Step 5: diet care by symptom
- Poor appetite: small, frequent meals and energy-dense snacks; make the most of the time of day when appetite is best.
- Nausea: cool or room-temperature food, fewer strong smells, dry crackers before getting up.
- Sore mouth: soft, moist textures; avoid acidic, spicy or very hot food.
- Taste changes: try plastic cutlery for a metallic taste and add herbs or lemon if tolerated.
- Low white cell count: strict food hygiene, well-cooked meat and eggs, washed produce.

If food alone is not enough, oral nutritional supplements come next. When the gut works but the patient cannot eat enough, enteral (tube) feeding is preferred over intravenous nutrition; parenteral nutrition is reserved for when the gut cannot be used.
Who does what in the team
Nurses usually carry out screening and weekly weights, dietitians complete the full assessment and plan, doctors look for treatable causes such as uncontrolled nausea, and pharmacists review medicines that affect appetite. In an assignment, showing how these roles fit together earns more credit than listing the tools in isolation.
A worked case
Mr K is 62 and has oesophageal cancer. He is 1.70 m tall and weighed 78 kg three months ago; today he weighs 70 kg. That is 8 kg, or about 10.3% of his usual weight, lost in three months, well past the six-month threshold. His BMI is 70 ÷ 1.70² ≈ 24.2, which looks reassuringly normal and shows exactly why BMI alone misleads. He reports eating about half his usual meals because food sticks when he swallows. On examination his temples look hollow and his upper-arm muscle has thinned. His albumin is low, but so is his CRP, so inflammation alone does not explain it.
Put together, this points to SGA grade C. A sensible plan would be a texture-modified, energy-dense diet with oral nutritional supplements, weekly weights, and early discussion of a feeding tube if swallowing worsens before surgery. Writing a case like this, with the numbers shown, demonstrates more understanding than describing the tools in the abstract.
Refeeding syndrome: the risk when feeding restarts
When someone who has eaten very little for days starts receiving nutrition again, shifts in phosphate, potassium and magnesium can cause dangerous heart and breathing problems. This is refeeding syndrome. NICE guidance in the UK advises identifying high-risk patients, such as those who have eaten little or nothing for more than five days, starting feeding slowly, and monitoring electrolytes closely. Mentioning it in an assignment shows you understand that more food is not automatically safer.
Nutrition across the treatment journey
Priorities change with the stage of care. Before surgery, the aim is to build reserves, and enhanced recovery programmes encourage patients to keep eating and drinking until shortly before the operation. During chemotherapy and radiotherapy, the goal is to limit weight loss while side effects come and go. In palliative care, the focus moves to comfort and enjoyment of food, and strict targets may no longer be appropriate. An assignment that recognises these shifts reads as clinically mature.
How much energy and protein?
The ESPEN guideline on nutrition in cancer patients (2017) suggests that, unless measured, energy needs can be estimated at roughly 25–30 kcal per kilogram of body weight per day, and that protein intake should be above 1 g/kg and, if possible, up to 1.5 g/kg per day. For Mr K at 70 kg, that means about 1,750–2,100 kcal and at least 70 g of protein a day, a useful figure to include when you set targets. Showing the calculation is a simple way to turn a general plan into a measurable one, and it gives you something concrete to re-check at each weekly weigh-in.
Student money tip on CampusDown Repair Up: How to Plan a Home Repair Budget.
Families often ask whether they should cut out sugar or follow special 'anti-cancer' diets. It is fair to explain that restrictive diets make it harder to meet energy and protein needs and can speed up weight loss, so any change should be discussed with the dietitian first.
Reviewed by the CampusDown editorial team, November 2026. Sources: Fearon K. et al. (2011), The Lancet Oncology 12(5); Detsky A. S. et al. (1987), JPEN 11(1); BAPEN, Malnutrition Universal Screening Tool; WHO, BMI classification.
FAQ
How much weight loss is significant?
Unintentional loss of 5% or more in one month, or 10% or more in six months, is usually treated as clinically significant.
Why is albumin not enough on its own?
Its half-life is about three weeks and inflammation lowers it, so it reacts slowly and can mislead; read it alongside CRP and faster markers like prealbumin.
What does SGA grade C mean?
Severe malnutrition: marked weight loss, reduced intake and clear loss of muscle and fat on examination.
Which screening tool is used in the UK?
Many hospitals and community services use MUST, the Malnutrition Universal Screening Tool developed by BAPEN.