
Is Breast Budding at Age 7 Normal? Precocious Puberty Age Cutoffs, Causes, Bone Age X-rays and GnRH Agonist Treatment in the US and UK
- Precocious puberty is traditionally defined as puberty starting before age 8 in girls and before age 9 in boys.
- Doctors separate brain-driven central cases from peripheral ones using growth charts, bone age X-rays and hormone tests.
- GnRH agonists are used only when puberty is central, progressing and threatening height or wellbeing.
Contents
Precocious puberty means that the body starts the changes of puberty unusually early, which US and UK pediatric endocrinologists traditionally define as before age 8 in girls and before age 9 in boys. A small breast bud on a 7-year-old, a sudden growth spurt in a second grader or body odor that seems years ahead of schedule are the kinds of signs that bring families to a pediatrician. This guide explains the age cutoffs used by the American Academy of Pediatrics (AAP) and the Pediatric Endocrine Society (PES), the difference between central and peripheral precocious puberty, the tests doctors order and when treatment actually makes sense.
Parents are often surprised to learn that puberty in general has been drifting earlier for decades. A landmark 1997 study of more than 17,000 American girls in pediatric offices found breast development starting earlier than textbooks claimed, especially among Black and Hispanic girls. That is one reason why experts now debate where "early" really begins, and why a careful evaluation matters more than a single birthday cutoff.
What age counts as precocious puberty in the US and UK?
Puberty begins when the hypothalamus in the brain starts releasing gonadotropin-releasing hormone (GnRH) in pulses. That signal tells the pituitary gland to release LH and FSH, which in turn wake up the ovaries or testes. When this hormonal chain switches on more than about two standard deviations earlier than average, doctors call it precocious puberty.
Student money tip from CampusDown Life UpHow to Find Unclaimed Money in Your Name — How to find unclaimed money in your name for free: official state databases via NAUPA and MissingMoney.com, federal searches like Treasury…
| Group | Traditional cutoff | Typical first sign |
|---|---|---|
| Girls | Before 8 years | Breast budding (thelarche), then pubic hair and a growth spurt |
| Boys | Before 9 years | Testicular enlargement to 4 mL or more, then pubic hair and voice change |
| Early periods | Menarche before about 10 years | Usually follows two to three years after breast budding |
Some US experts have suggested lowering the threshold for girls to 7, or to 6 for Black girls, based on newer population data. The PES and most pediatric endocrinologists still use 8 and 9 as the point at which evaluation is warranted, while recognizing that a healthy 7-year-old with slow, mild changes may simply be on the early side of normal.
Doctors describe how far puberty has progressed using Tanner stages, a five-step scale from prepubertal (stage 1) to adult (stage 5) for breast, genital and pubic hair development. A child who moves from stage 2 to stage 3 within months is more concerning than one who has stayed at stage 2 for a year.

Central or peripheral: what is the difference?
The single most important question in an evaluation is whether puberty is being driven by the brain or by hormones coming from somewhere else. The answer changes both the tests and the treatment.
| Feature | Central (GnRH-dependent) | Peripheral (GnRH-independent) |
|---|---|---|
| Mechanism | The brain's puberty clock turns on early | Sex hormones come from the ovaries, testes, adrenal glands or outside sources |
| Who gets it | Most common in girls, usually with no identifiable cause | Less common; causes include ovarian cysts, adrenal disorders and McCune-Albright syndrome |
| Key lab finding | LH rises after a GnRH or leuprolide stimulation test | LH stays low while estrogen or testosterone is high |
| Treatment | GnRH agonists if criteria are met | Treat the underlying source; GnRH agonists do not work |
Here is a twist parents rarely hear: girls are far more likely to have central precocious puberty, but in boys an underlying problem such as a brain lesion is found more often. That is why many US and UK centers order a brain MRI for almost every boy with central precocious puberty, and for girls who start especially young, often before 6.
Skimming the section headings first makes a long guide much easier to map out. Try writing down one question of your own as you read.
What causes puberty to start early?
In most girls with central precocious puberty, no specific cause is found, a situation called idiopathic. Researchers have identified several factors that shift the timing, though none of them explains every case.
- Body fat: higher BMI in girls is linked to earlier breast development, possibly through the fat-related hormone leptin.
- Genetics: family timing explains a large share of when puberty starts, and mutations in genes such as MKRN3 run in some families.
- Endocrine-disrupting chemicals: research has looked at substances such as certain pesticides, phthalates and BPA, but evidence in humans is mixed.
- Stress and adversity: early life stress and family conflict are associated with earlier puberty in several studies.
- International adoption: children adopted from lower-income countries into the US or Europe show higher rates of early puberty.
Some popular worries hold up less well. Soy milk and chicken are frequently blamed online, yet studies have not shown that normal amounts in the diet cause precocious puberty. Accidental exposure to an adult's testosterone gel or estrogen cream, on the other hand, is a well documented and often overlooked cause of peripheral puberty, so doctors will ask about creams and supplements in the home. To understand why these substances matter, it helps to know how estrogen acts on breast and bone tissue.
Boys behave a little differently: obesity is not clearly linked to earlier puberty in boys and may even delay it in some studies, another reason to investigate rather than assume.
How do doctors diagnose it?
The evaluation usually starts with a pediatrician and then moves to a pediatric endocrinologist. It has four parts, and parents can speed things up by bringing past growth measurements.
History and growth chart
The doctor asks when changes began, whether there are headaches or vision problems, and whether any hormone products are in the house. Plotting height on CDC charts in the US or UK-WHO growth charts in Britain often shows the clue: a child crossing upward from, say, the 50th to the 90th percentile.
Bone age X-ray
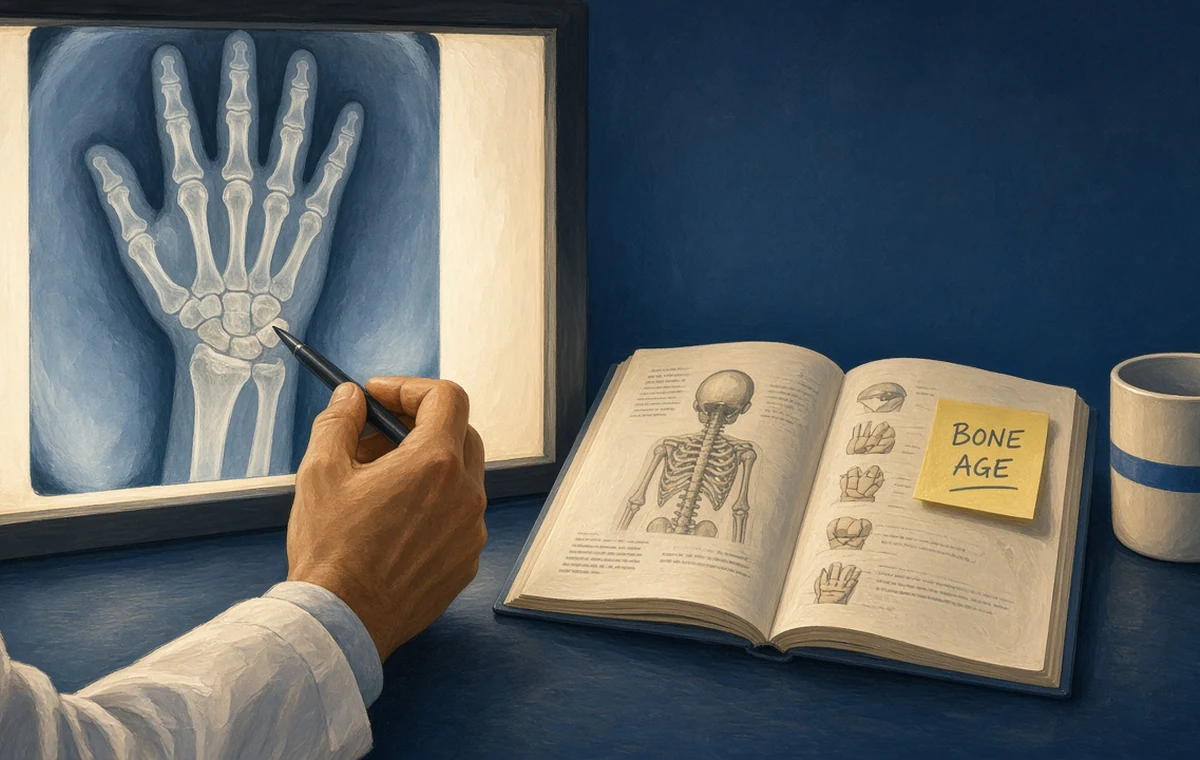
A single X-ray of the left hand and wrist lets a radiologist compare the child's bones with reference images, usually from the Greulich and Pyle atlas. If a 7-year-old has a bone age of 10, puberty hormones have been acting for a while and adult height may be at risk because growth plates close early.
Blood tests and stimulation testing
Morning blood samples measure LH, FSH, estradiol or testosterone. Because a single LH value can be borderline, many centers perform a stimulation test, giving a dose of a GnRH agonist and checking LH over the next hours to see whether the brain's puberty axis is fully awake.
Imaging when needed
A pelvic ultrasound can show the size of the uterus and ovaries in girls, and a brain MRI looks for lesions that can trigger central puberty.
Who needs GnRH agonist treatment?
Not every child with early puberty needs medication. Treatment is aimed at children whose puberty is clearly central and progressing, whose bone age is advancing fast enough to threaten adult height, or who are struggling emotionally, for example a 6-year-old who is distressed by early periods.
GnRH agonists work by overstimulating the brain's receptors so that they stop responding, which pauses puberty. In the US the common options are leuprolide injections given every one, three or six months, triptorelin every six months, and a histrelin implant placed under the skin of the upper arm that lasts about a year. In the UK, triptorelin and leuprorelin injections every one to three months are the most common choices on the NHS. Treatment usually continues until around the typical age of puberty, after which puberty resumes within months.
Cost and access differ sharply. On the NHS the evaluation and medication are free at the point of use, though families may wait for a specialist appointment. In the US the medication can cost thousands of dollars a year, so families often need prior authorization from their insurer or Medicaid before the first dose.
What can parents do while they wait?
Watchful waiting is a legitimate plan when changes are slow, and lifestyle habits still help a child feel well. A healthy weight, daily physical activity, good sleep and keeping adult hormone creams out of reach are sensible steps for every family.
Student money tip on CampusDown Life Up: How to Find Unclaimed Money in Your Name.
Just as important is how children feel. Early breast development or body odor can make a second grader self-conscious, so simple age-appropriate explanations, a supportive school nurse and reassurance that their body is healthy go a long way. If changes are speeding up, or there are headaches or vision changes, book a review sooner rather than later.
Reference: Carel, J.-C., and Léger, J. (2008). Precocious puberty. The New England Journal of Medicine, 358(22), 2366-2377, a widely cited review of the diagnosis and treatment of precocious puberty.
FAQ
What age is considered precocious puberty?
US and UK pediatric endocrinologists usually evaluate puberty that begins before age 8 in girls or before age 9 in boys.
What is the first sign in boys?
Testicular enlargement to a volume of 4 mL or more, which a doctor checks with an orchidometer, usually comes before pubic hair or voice changes.
Why is a hand X-ray done?
A bone age X-ray shows how mature the skeleton is compared with the child's actual age, which helps predict adult height and judge how long hormones have been active.
Does soy milk cause early puberty?
Studies have not shown that normal dietary amounts of soy cause precocious puberty. Accidental exposure to adult hormone creams or gels is a more important cause to rule out.
Will my child stop growing on GnRH agonist treatment?
Growth usually slows to a prepubertal rate, and bone age advances more slowly. After treatment stops, puberty restarts within months and many children reach a better adult height.